What LPA Means in Your 23andMe Raw Data
LPA in 23andMe raw data is a genetic flag for lipoprotein(a), not a heart diagnosis. The next step is an Lp(a) blood test.
When you see LPA in 23andMe raw data, it means the gene for apolipoprotein(a), the protein that binds to LDL cholesterol to form lipoprotein(a), usually called Lp(a). The HealthOS free report includes LPA as an inherited heart-risk factor. It does not give an Lp(a) blood measurement. That is a genetic flag, not a blood measurement and not a heart diagnosis.
What does LPA mean in my 23andMe raw data?
A raw DNA file is not a blood test. It lists genotype calls at specific positions, not concentrations. When your file contains LPA markers such as rs10455872 or rs3798220 (on chips that include them), each call is a single-letter variant in or near the LPA gene. Carrying one or more risk-associated variants is linked to a higher inherited Lp(a) risk. These named SNPs may not be present in every 23andMe export. Absence of those SNPs does not rule out high Lp(a) risk.
The LPA gene has a repeated region called KIV-2. Fewer repeats mean the liver makes more apolipoprotein(a), which raises Lp(a). SNP chips cannot count those repeats reliably. They read nearby signposts that tag part of that repeat variation. That is why the raw data is useful but incomplete. It catches a signal, not the full number.
| Raw LPA genotype | Lp(a) blood test | |
|---|---|---|
| What it reads | Single-base markers in or near LPA | Concentration of Lp(a) particles |
| What it answers | Inherited tendency | Actual level now |
| Units | Allele calls, no units | mg/dL or nmol/L |
| Stability | Fixed from birth | Mostly stable in adults |
Scroll the table sideways for the rest →
The raw marker shows tendency. The blood test shows the actual level.
The genotype tells you whether your inherited Lp(a) risk is more likely to run high. The blood test tells you whether it actually does.
Why a standard cholesterol panel misses it
A routine lipid panel usually reports total cholesterol, LDL cholesterol, HDL cholesterol and triglycerides. It does not separately measure Lp(a). The LDL cholesterol value includes the cholesterol carried inside Lp(a), but it does not tell you how much of that LDL is Lp(a). Two people with the same LDL cholesterol can have very different Lp(a) risk.
Lp(a) is reported in mg/dL or nmol/L. Many labs flag values above roughly 50 mg/dL (about 125 nmol/L) as high, though risk rises continuously before that. Because levels are mostly genetically determined, they are stable in adults. Diet and fasting do not move them much. Some studies report a modest increase in Lp(a) with statins in some people. That stability makes a single well-timed blood test informative.
Does a high-risk LPA genotype mean I have heart disease?
No. The genotype is a flag, not a diagnosis. A risk-associated variant means your inherited tendency is higher, but some carriers still have normal Lp(a). The opposite also happens: a normal LPA genotype can accompany high Lp(a) because the chip did not capture the KIV-2 repeat count or another relevant variant.
If your raw data flags LPA, the next question is not whether you have heart disease. It is what your actual Lp(a) number is. The answer comes from a blood test. You do not need to assume your genotype is your fate, and you also should not assume a reassuring genotype clears you.
When the simple answer does not hold
Common LPA tag SNPs may predict Lp(a) less consistently across ancestries. Prediction can vary by ancestry, chip, and reference panel. The same KIV-2 repeat biology matters, but KIV-2 repeat biology is not fully captured by SNP chips and the signposts on a standard SNP chip may not capture it equally.
Some health conditions and life stages may also affect measured Lp(a), so a high Lp(a) blood result should be read in context, not as a standalone verdict. The genetic result is the more stable piece.
What to do with your raw data now
- If your LPA genotype is flagged, an Lp(a) blood test is worth asking a doctor about. One measurement is usually enough because the level is stable.
- If the blood test is high, discuss overall cardiovascular risk with a doctor. The genotype alone is not the treatment target.
- If the blood test is normal, the genotype is background information, not a to-do list.
The common mistake is treating a high-risk LPA genotype as a heart diagnosis, or a normal genotype as a free pass. Both are wrong.
A raw file can tell you the flag is there. Only a blood test tells you the number.
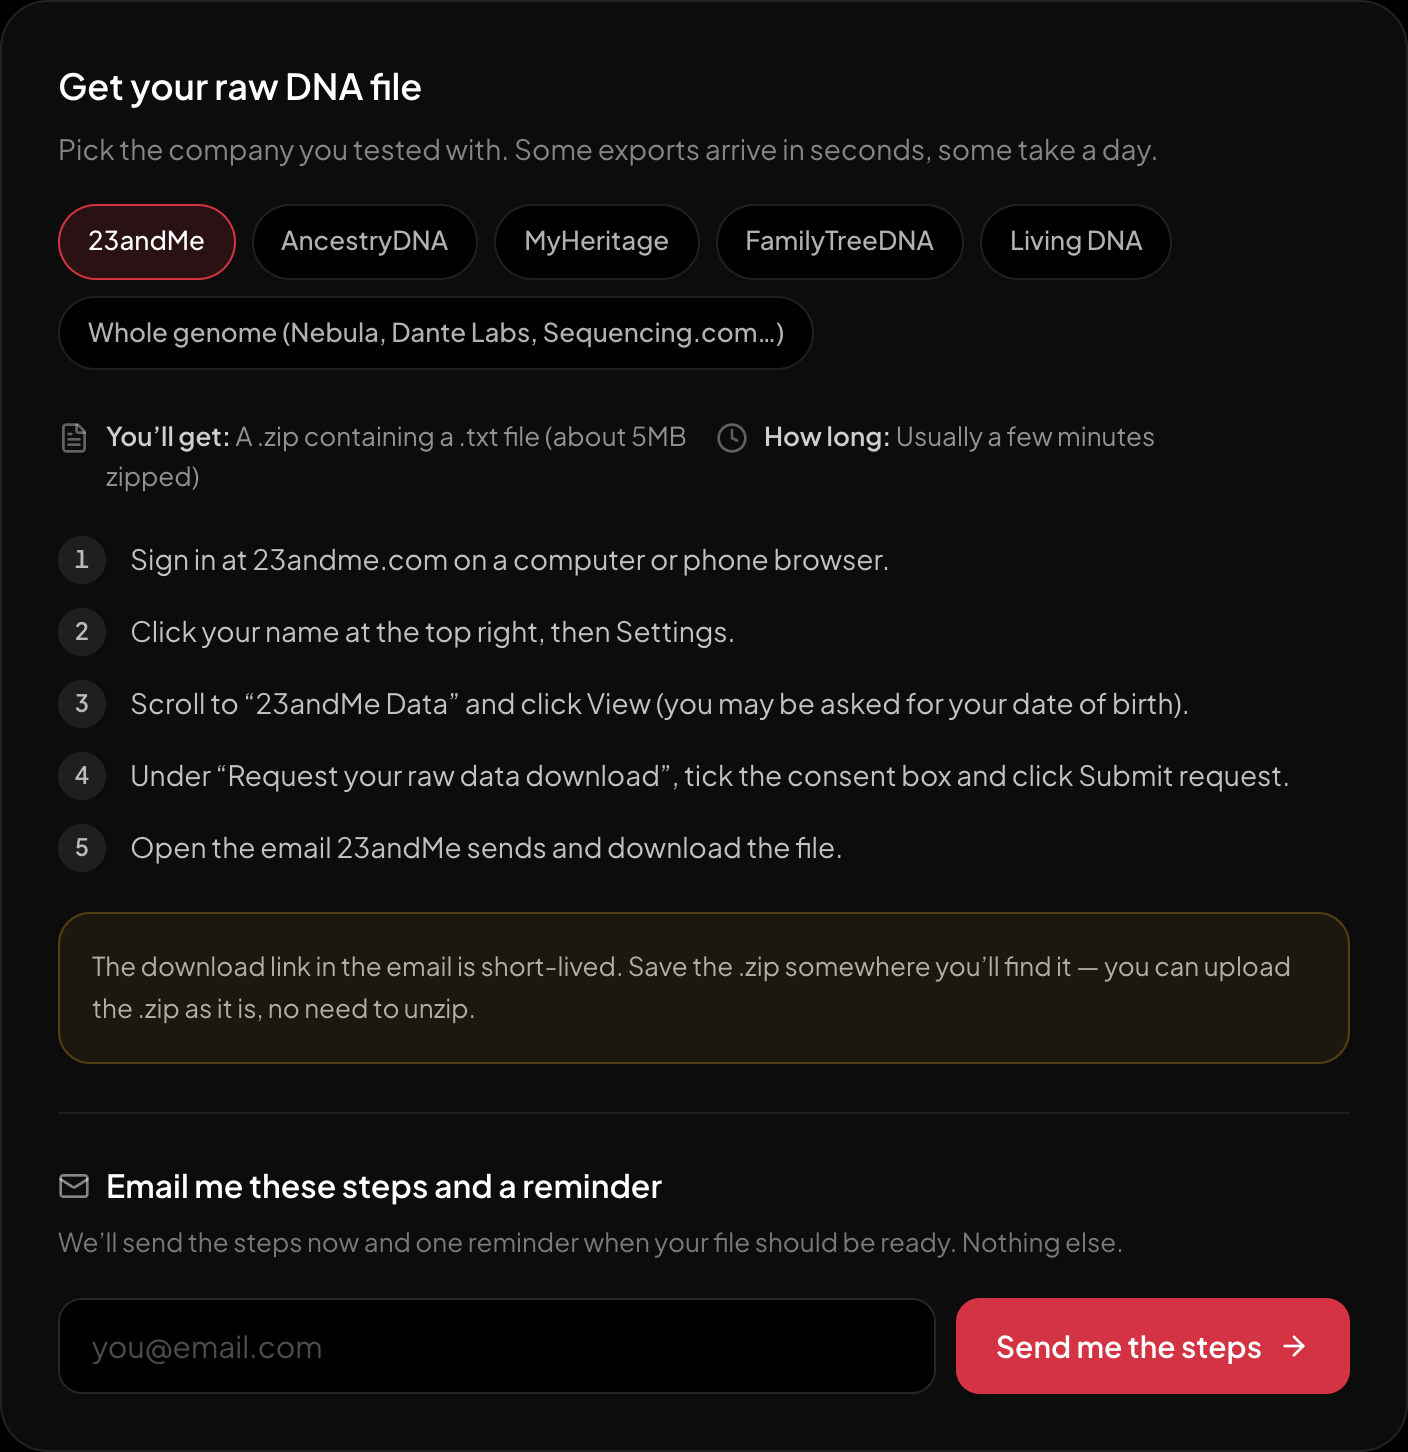
The download steps for 23andMe, on the page itself.
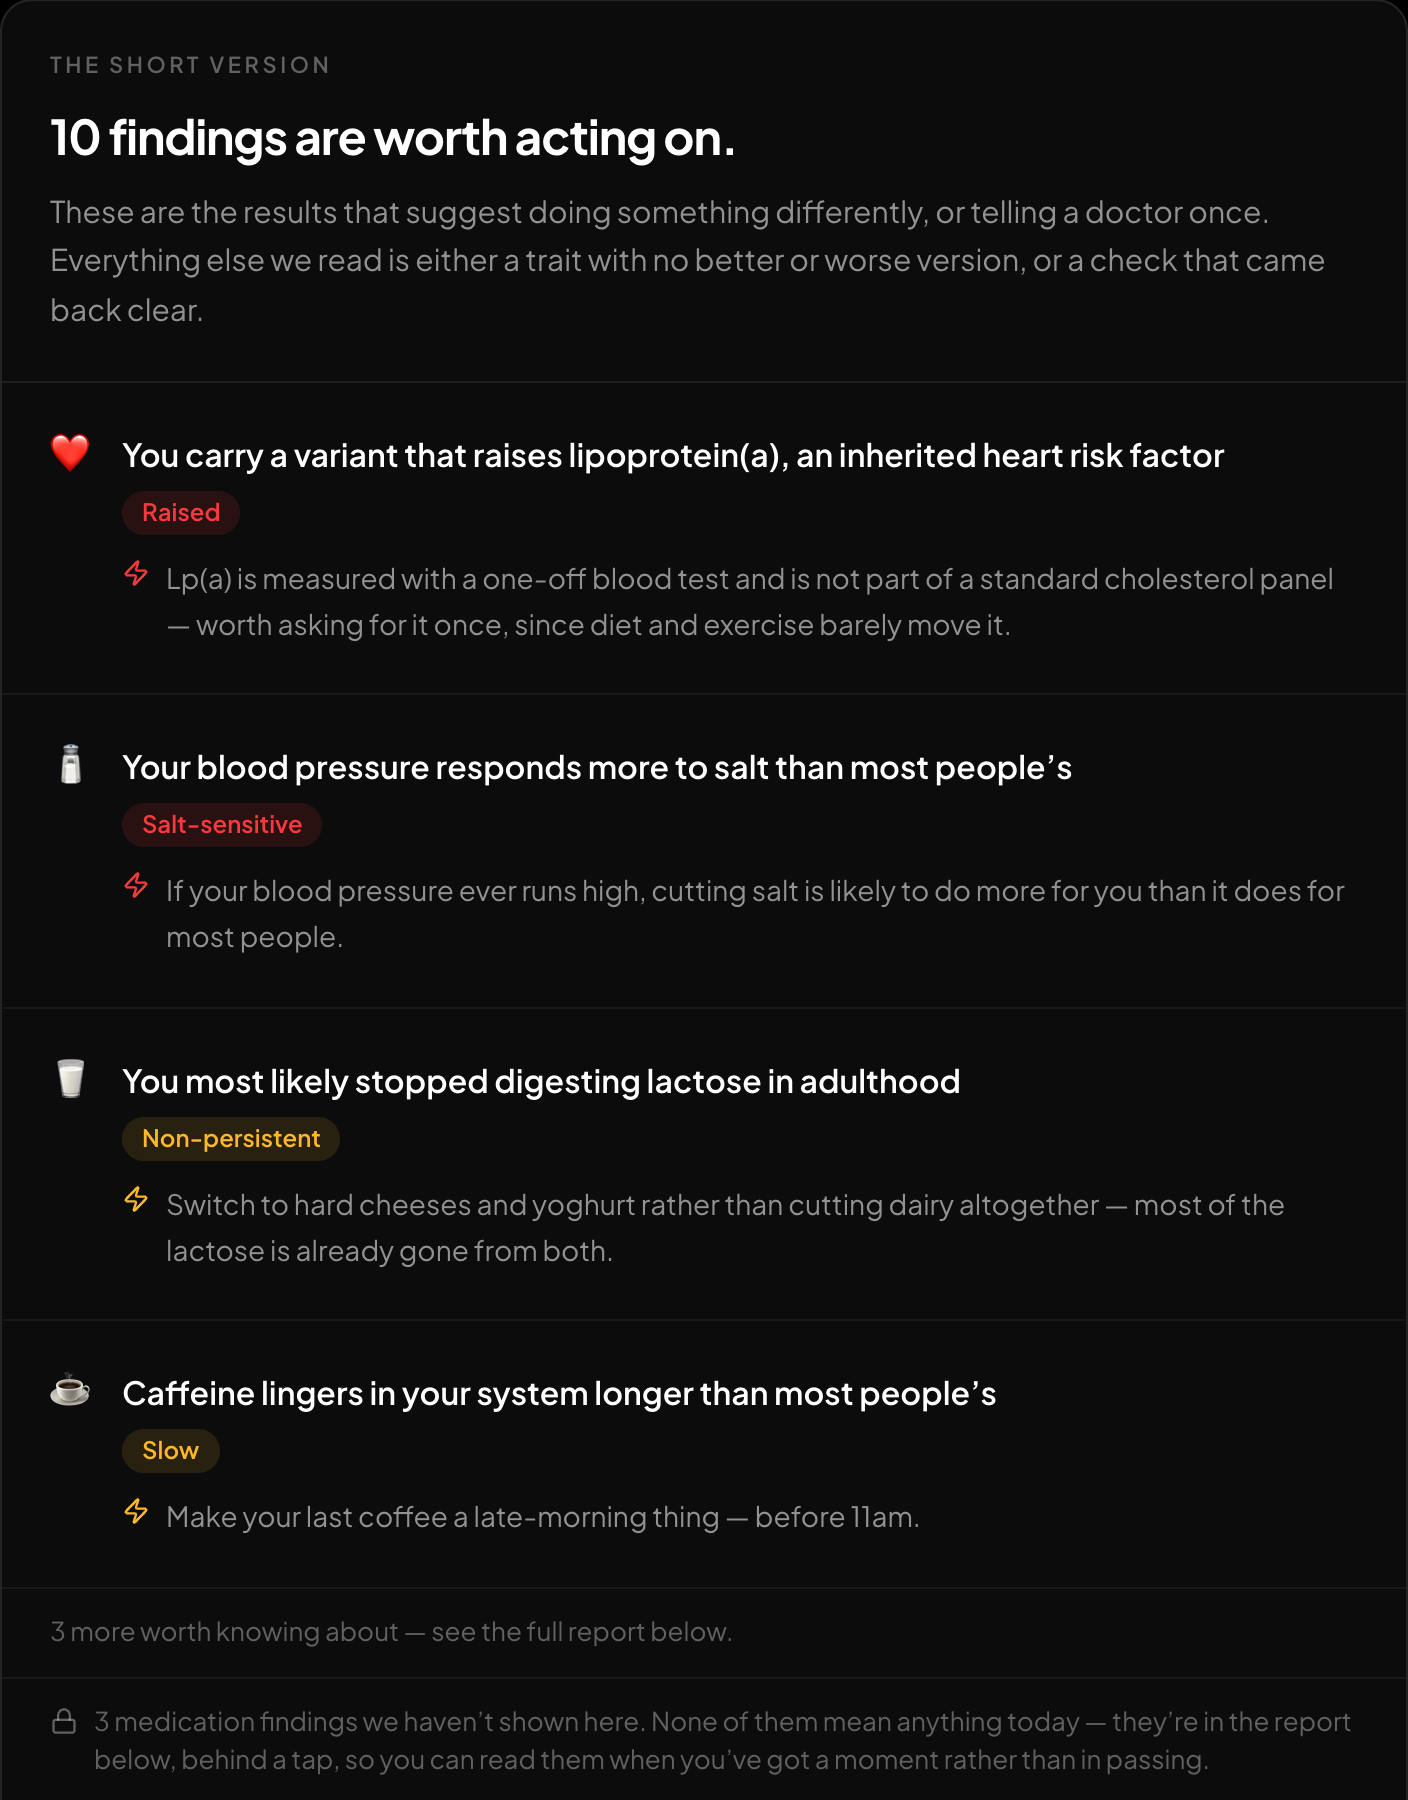
The short version: what is worth acting on, first.
The free DNA tool at HealthOS /dna accepts common raw DNA files, including 23andMe, AncestryDNA, MyHeritage, FamilyTreeDNA, Living DNA, WeGene and whole-genome VCFs. The trait and health report is read in the browser without upload. Ancestry is optional and needs a server. If your VCF lacks rsIDs, the report is ancestry only; the trait report needs rsIDs. If you want to see your own LPA flag and the rest of the findings, run the file there.
New to raw DNA files? Start with the full guide: How to Download & Analyze Your 23andMe Raw Data Free
Written by
HealthOS Research